
This post contains affiliate links. If you click a link and make a purchase, I may earn a small commission at no extra cost to you. I only recommend products I genuinely believe in. Thank you for supporting Amoria Style!
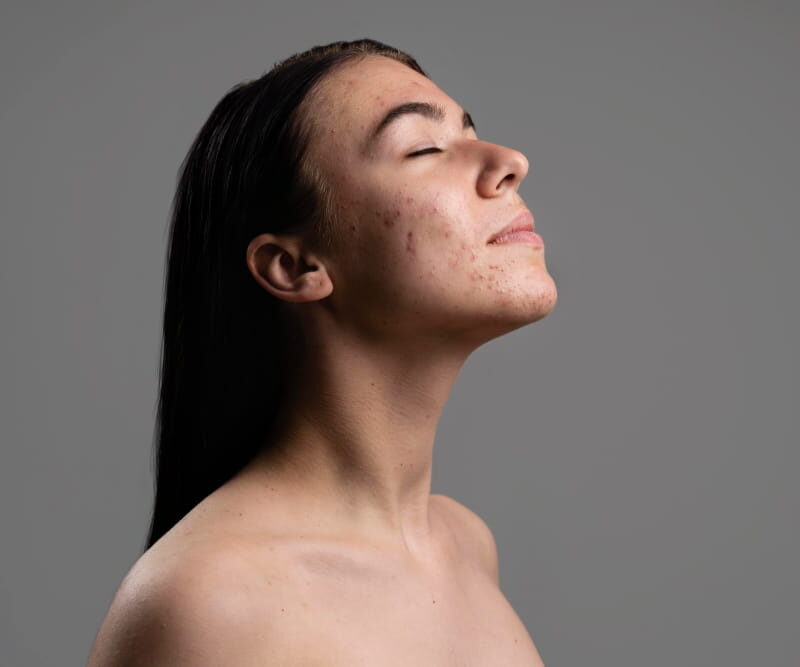
Jawline breakouts get treated as a single category online, usually labeled simply as “hormonal acne,” with advice that doesn’t always match what’s actually happening. In reality, breakouts along the jawline can come from at least three genuinely different mechanisms — hormonal fluctuation, mechanical friction, and occlusion from masks, helmets, or phone calls — and each one needs a different response. Treating friction-related breakouts with hormonal acne advice, or vice versa, is a common reason people feel like nothing works despite trying everything.
Here’s how to actually tell which one you’re dealing with, and why it matters.
Why the Jawline Specifically
Before separating the causes, it’s worth understanding why this particular area is so breakout-prone in the first place. The jawline sits at the intersection of several factors: it has a relatively high concentration of androgen-sensitive sebaceous glands (which makes it particularly responsive to hormonal fluctuation), it’s an area of frequent mechanical contact (phones, masks, hands, pillows), and it’s often under-treated in skincare routines that focus more attention on the central face and forehead.
This combination of hormonal sensitivity and frequent physical contact is exactly why jawline breakouts have multiple possible causes that can look visually similar but require different responses.

Hormonal Jawline Acne — What It Actually Looks Like
Hormonal acne along the jawline tends to follow a recognizable pattern that distinguishes it from the other two causes.
Timing: Often cyclical, appearing or worsening in the days leading up to menstruation, though it can also relate to other hormonal shifts (starting or stopping hormonal birth control, perimenopause, conditions like PCOS). The cyclical pattern, when present, is one of the clearest distinguishing signals. (source)
Appearance: Tends to be deeper, often presenting as tender, sometimes painful cystic or nodular bumps beneath the skin surface rather than surface-level whiteheads. These can take longer to resolve than typical surface acne and are more likely to leave post-inflammatory marks.
Distribution: Frequently appears along the lower jawline and chin specifically, sometimes extending down the neck, in a pattern that’s fairly symmetrical on both sides of the face.
What helps: Hormonal acne typically responds best to ingredients and approaches that address oil production and inflammation at a systemic or hormonal level — which is a different category of intervention than surface treatment alone. Salicylic acid can help manage the surface symptoms, but the underlying driver often needs to be addressed through other means (dietary factors for some people, hormonal birth control adjustments for others, or in persistent cases, a conversation with a dermatologist about prescription options like spironolactone, which specifically targets androgen activity). Surface treatments alone frequently underperform for genuinely hormonal breakouts because they’re not addressing the root cause.
Friction Acne (Acne Mechanica) — What It Actually Looks Like
This category gets far less attention than hormonal acne despite being extremely common, particularly for anyone who spends significant time on the phone, wears chin straps for sports or work, or has habits involving repeated hand-to-jaw contact.
Timing: Less cyclical, more directly tied to specific activities or habits — appearing or worsening after periods of increased phone use, helmet or strap wearing, or other repeated contact, rather than following a hormonal calendar.
Appearance: Tends to be more superficial than hormonal acne — smaller, more numerous bumps rather than deep cystic lesions, sometimes resembling a rash-like cluster rather than distinct individual breakouts.
Distribution: Often asymmetrical, more pronounced on whichever side of the face has more contact — the side you hold your phone against, for example, or wherever a strap or helmet creates the most friction and pressure.
What helps: This category responds well to mechanical intervention rather than internal treatment — reducing the actual friction and pressure is more effective than any topical product. Using speakerphone or headphones instead of holding a phone against the jaw, cleaning phone screens regularly (they accumulate oil and bacteria that transfer directly to skin with each call), and reassessing whether straps or helmets can be adjusted or padded to reduce direct skin pressure. Salicylic acid or benzoyl peroxide can help manage active breakouts, but without addressing the mechanical cause, the breakouts will simply recur in the same friction-affected areas.
Mask-Related Acne (Maskne) — What It Actually Looks Like
This category became widely recognized during periods of extended mask-wearing but remains relevant for anyone who wears masks regularly for work, health reasons, or extended periods of any kind, including those who wear face coverings during exercise or in certain occupational settings.
Timing: Directly correlated with mask-wearing duration — worsens with longer or more frequent wear, often improves relatively quickly (within days to a couple of weeks) once mask-wearing frequency decreases or proper management is introduced.
Appearance: Often a mix of whiteheads, blackheads, and inflamed bumps, frequently accompanied by a generally irritated, sometimes rash-like texture across the entire covered area rather than isolated breakouts. The combination of occlusion (trapped heat, moisture, and breath) and friction (the mask material against skin) creates a distinct mechanism from either hormonal or pure friction acne alone.
Distribution: Matches the exact coverage area of whatever mask or covering is worn — typically nose, mouth, chin, and jawline in a pattern that closely follows the mask’s edges, often with visible irritation specifically where the mask edge sits against skin.
What helps: Reducing occlusion time where possible, switching to breathable, natural fiber materials (cotton performs better than synthetic blends for skin contact in this context), washing reusable masks after each use rather than reusing them multiple times, and simplifying skincare underneath the mask — heavy makeup or rich moisturizer under a mask compounds the occlusion problem rather than helping it. A lightweight, non-comedogenic moisturizer and minimal makeup in the mask-covered area reduces the combined burden of product occlusion plus mask occlusion.

Why Misidentifying the Cause Wastes Time and Money
The most common frustration people describe — trying numerous products with no improvement — very often comes down to treating the wrong mechanism. Salicylic acid and consistent skincare can meaningfully help mask-related and friction-related breakouts because the issue is largely about surface-level buildup, occlusion, and bacterial transfer. The same approach often underperforms for genuinely hormonal breakouts because the surface-level intervention isn’t addressing the hormonal driver underneath.
This is why someone with hormonal jawline acne can follow a thorough, well-executed skincare routine and still struggle, while someone with friction acne might find that simply changing how they hold their phone resolves breakouts that months of products didn’t touch.
It's Often More Than One Cause at Once
These three categories aren’t mutually exclusive, and a meaningful number of people dealing with jawline breakouts are managing some combination of more than one simultaneously — hormonal sensitivity that’s made worse by friction from a phone habit, for example, or maskne that’s compounded by an already hormonally reactive jawline.
If addressing one identified cause improves things partially but doesn’t fully resolve the breakouts, it’s worth considering whether a second mechanism is also contributing rather than assuming the first intervention simply didn’t work.

The information in this post is based on personal research and experience and is intended for educational purposes only. It is not a substitute for professional medical or dermatological advice, diagnosis, or treatment. Always consult a qualified healthcare provider before making changes to your skincare routine or health practices, especially if you have a medical condition or sensitivity.
